
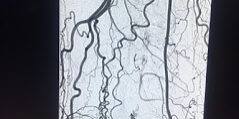
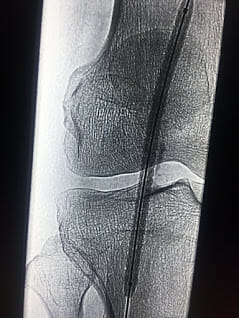
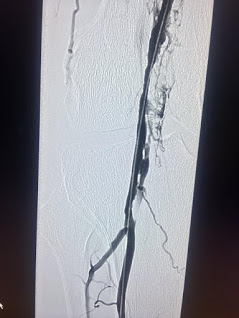
Popliteal Artery chronic total occlusion in the patient with CLI. Novice use of Gore TIGRIS sent following challenging recanalization. Superior flexibility of that system and ePTFE coating of stent struts prove important in addressing chronic occlusion of the Popliteal Artery.



Listen to the Latest Podcast
Listen to the latest podcast featuring Dr Marek Garbowski and Medical Forum, WA’s independent monthly publication for health professionals.
Get in Touch

About the Author: Dr Marek Garbowski
Dr Marek Garbowski, MBBS, FRACS (Vasc), is a Vascular and Endovascular Surgeon and the founder of Perth Vascular Clinic, which he established in Subiaco in 2006.
He completed his MBBS in 1994 and trained across Australia and New Zealand before being awarded Fellowship of the Royal Australasian College of Surgeons in Vascular Surgery in 2005. He performs both open vascular surgery and minimally invasive endovascular procedures, with particular interests in carotid stenting, complex aortic aneurysm repair, endovenous treatment of varicose veins and the management of leg and foot ulcers.
Dr Garbowski consults in Subiaco and Joondalup, heads the Vascular and Endovascular Surgery Department at Joondalup Health Campus, and teaches at UWA and Notre Dame.
Millions of Women suffer from Pelvic Pain
In some cases, this pain can be caused by Pelvic Venous Disorders (also known as Pelvic Congestion Syndrome).
If you're in pain and can't seem to find any answers, read our guide and find out more.
Frequently Asked Questions
A chronic total occlusion (CTO) of the popliteal artery with critical limb ischaemia (CLI) represents a severe blockage behind the knee that has caused critically reduced blood flow to the foot and lower leg. CLI is characterised by rest pain, non-healing wounds, or tissue loss, and represents a limb-threatening condition requiring urgent intervention.